
Approving Bariatric Surgery at Lower BMI May Improve Patient Outcomes
As more Americans turn to bariatric surgery for weight loss, a new study suggests they may not want to wait until their BMI exceeds 40 to reap the biggest benefits.
11:00 AM
Author |
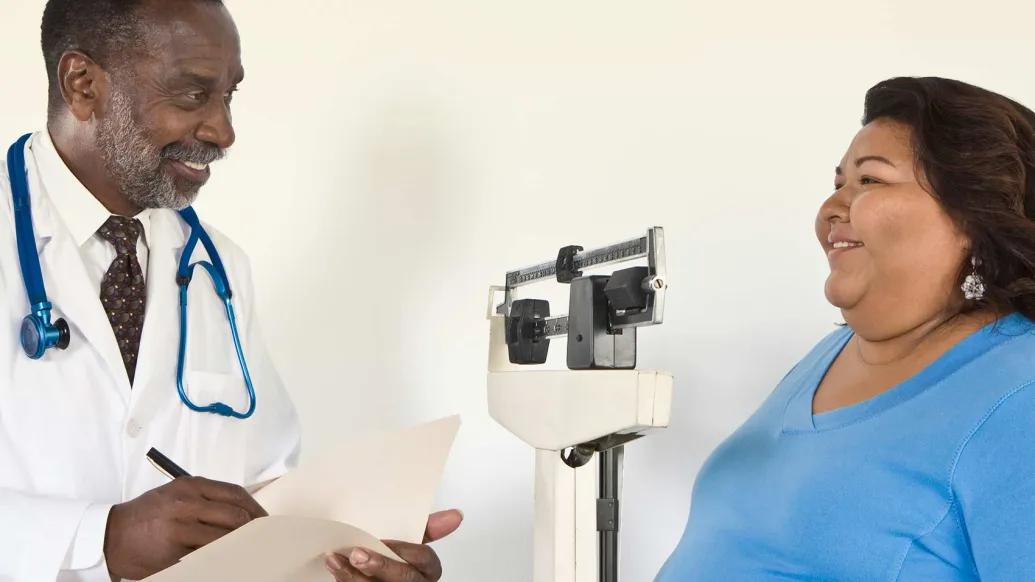
The struggle to escape obesity takes more and more Americans to a surgeon's door in search of bariatric surgery — a move that recipients hope will alter their metabolism, help them shed pounds and reduce the risk of weight-related health issues.
A large new study has found that only 1 in 3 patients who have the operation succeed in getting their body mass index below 30, the cutoff for obesity, in the first year.
One major factor: a person's height-to-weight ratio prior to the operation.
Odds of achieving a BMI under 30 in one year, the study found, were much higher for those who had their weight-loss operation while still below the "morbid obesity" BMI level of 40.
On the other end of the spectrum, less than 9 percent of those with a BMI of 50 or higher got down to 30 or below in the first year after surgery.
The findings, published in JAMA Surgery by a team from the University of Michigan, Wayne State University and Henry Ford Health System, could help surgical teams counsel prospective patients about realistic expectations and the best timing for surgery.
"Despite its proven safety and efficacy, bariatric surgery remains highly regulated and can be misunderstood by referring physicians and patients alike," says lead author Oliver Varban, M.D., director of bariatric surgery at Michigan Medicine, U-M's academic medical center. "This study provides additional data to help counsel patients appropriately about weight-loss expectations after bariatric surgery."
The authors also say their results have implications for how insurers cover weight-loss surgery, including requirements that patients are unable to achieve a specific BMI under medically supervised nonsurgical options before plans will approve coverage for surgery.
That's because reaching a BMI of 30 or lower gave a patient much better odds of escaping weight-related health risks, the study found.
Those who hit this level also were far more likely to report that they had stopped taking medication to control high blood pressure, blood sugar and cholesterol levels and achieved remission of sleep apnea, a breathing condition linked to obesity.
Waiting for a patient to reach a BMI over 50 only serves to limit the benefits of bariatric surgery as an intervention.
A statewide review
Varban and his colleagues studied first-year surgery results using detailed data from the medical charts of 27,320 Michigan residents who had some form of bariatric surgery over a 10-year period ending in mid-2015.
All had their operations with surgical teams taking part in Michigan's statewide bariatric surgery quality initiative, the Michigan Bariatric Surgery Collaborative, which is directed by study co-author Amir Ghaferi, M.D., M.S., and co-directed by the study senior author Jonathan Finks, M.D. The prospective data collection approach, and annual auditing of records, makes this source more complete than others used in prior studies.
The study included about half of all patients who had bariatric surgery under the direction of 70 bariatric surgeons based at the collaborative's 38 participating programs in hospitals of different sizes and types throughout the state. Only patients who had at least one year's worth of weight data and did not undergo a second operation to revise their first were included. Many also took a survey about health-related issues.
On average, according to the data, patients had a BMI of 48 before their operation and got down to 33 by the end of the first year. But only 9,700 patients, or 36 percent, achieved a BMI of 30 or lower.
The type of bariatric surgery patients had also played a key role, the study found.
Those whose surgeons chose to perform a sleeve gastrectomy, gastric bypass or duodenal switch operation were more likely to achieve a BMI under 30 than those who had adjustable gastric bands placed around their stomachs.
The group of patients that reached a BMI of 30 or lower didn't differ from the other patients in terms of overall surgical complication rates or rates of serious complications.
Not surprisingly, those who reached the recommended benchmark viewed the experience more favorably.
In all, 92 percent of those who hit a BMI under 30 in the first year said they were highly satisfied with their decision to have surgery, compared with 78 percent of those who didn't get to that level.
Implications for care
The National Institutes of Health has established a BMI of 40, or more than 100 pounds over a patient's ideal weight, as the lowest level for an individual to be considered for bariatric surgery.
For those already experiencing weight-related health conditions such as type 2 diabetes, high blood pressure, sleep apnea, high cholesterol or heart disease, the threshold is even lower: Those patients can have a BMI as low as 35, the NIH says.
Many insurers also require that patients first try medically supervised weight-loss programs, typically for a year or more, before they will cover the operation. Plans may enforce other conditions such as screening tests, psychological examinations and other documentation from a referring doctor.
Still, those reviews and restrictions vary.
Given their findings, then, the authors hope the study will better inform such referrals and shift coverage requirements to target the most suitable patients. An accompanying invited commentary in JAMA called the report "an important contribution to the field of metabolic and bariatric surgery."
One potential takeaway: Insurers could lower the BMI threshold, as many providers won't cover an otherwise healthy person whose BMI is lower than 40.
"Bariatric surgery is extremely safe and effective and should be considered as first-line therapy for patients with a BMI between 35 and 40," says Varban, an assistant professor of surgery at the U-M Medical School. "Waiting for a patient to reach a BMI over 50 only serves to limit the benefits of bariatric surgery as an intervention."
In addition to Varban, Finks and Ghaferi, who are members of the U-M Institute for Healthcare Policy and Innovation, the study's authors also include fellow members of the U-M Center for Healthcare Outcomes and Policy — Ruth Cassidy, M.A., and Aaron Bonham, M.S. — and Arthur Carlin, M.D., a bariatric surgeon at Henry Ford and a faculty member in the department of surgery at Wayne State.
The study was funded by Blue Cross Blue Shield of Michigan, which supports the Michigan Bariatric Surgery Collaborative.

Health Lab
Explore thousands of health news & research stories by visiting the Health Lab homepage for more.
Media Contact

Public Relations
Department of Communication at Michigan Medicine
Stay Informed
Want top health & research news weekly? Sign up for Health Lab’s newsletters today!
Featured News & Stories
Top 7 tips for choosing Medicare prescription drug coverage for 2027

Many older adults make Medicare decisions quickly and most don’t change plans, poll finds

What’s the latest on 7-OH and kratom availability and addiction care?
Better prenatal care data could help prevent maternal complications, experts say
Many hospitals still don’t do enough to prevent UTIs from catheters

