When blood pressure needs more control, what’s better: An additional drug or more of the same?
Study in veterans shows importance of personalizing the approach to intensifying treatment in sustainable ways.
5:00 PM
Author |
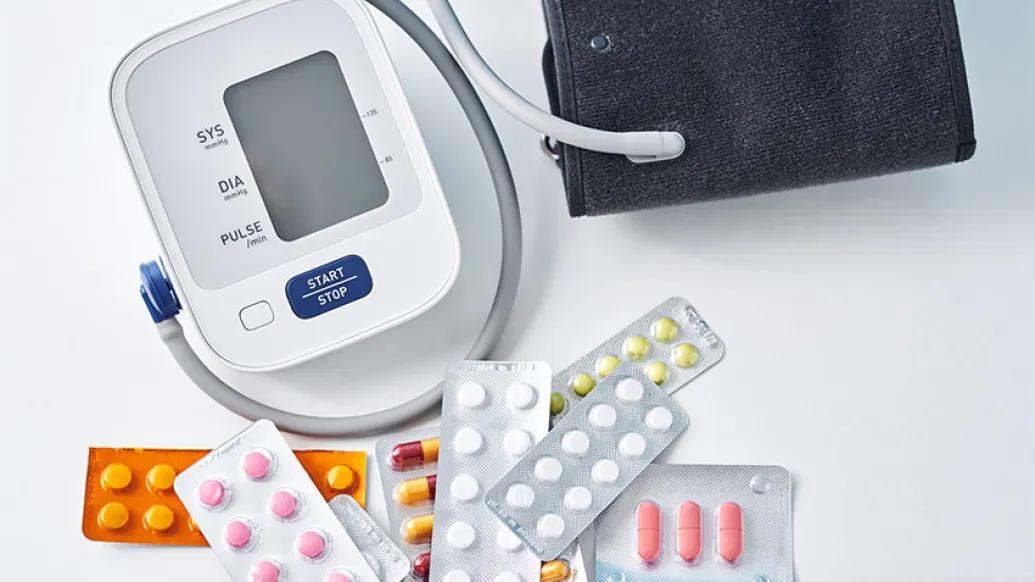
Nearly 34 million Americans have blood pressure that's still too high even though they take medicine to control it.
A new study may help them and their doctors decide whether to increase the dose of one of their existing drugs, or add a new one, to bring down their pressure and lower their risk of future health problems.
In a look back at data from nearly 179,000 veterans over age 65 who received treatment over two years at VA hospitals nationwide, researchers find that patients have a better chance of sticking to their medication regimen if their doctor maximizes the dosage of one of the drugs they're already taking. They also found that both strategies decrease blood pressure, but adding a new medication has a very slim advantage over increasing the dose of an existing medication, despite some of the patients being unable to stay on the new medication.
SEE ALSO: Harnessing healthy behaviors to prevent dementia
In the end, the researchers say, the new findings could add to discussions between physicians and patients whose blood pressure remains elevated despite starting medication treatment.
The findings, published in the Annals of Internal Medicine by a team from the University of Michigan and the VA Ann Arbor Healthcare System, focus on patients whose initial systolic blood pressure was above 130 mm Hg.
By looking back at VA and Medicare data, the researchers were able to see patterns in treatment and blood pressure readings over time, in a kind of natural experiment. All the patients were taking at least one blood pressure medication at less than the maximum dose and had a treatment intensification at the start of the study period, indicating that their physicians thought they needed more intense treatment.
These results show that in older patients, we have further opportunity to tailor choices in intensifying drug therapy for hypertension, depending on the individual patient's characteristics.Lillian Min, M.D., M.S.H.S.
Because intensification of blood pressure treatment can come with risks – whether a drug interaction if a new drug is added, or an electrolyte imbalance with high doses, or fainting and falling if a person's pressure gets too low – such decisions must be carefully made.
This is the first time a study has directly compared the effects of the two approaches, said first author Carole E. Aubert, M.D., M.Sc., a general internist from Bern University in Switzerland who performed much of the research while a scholar at the U-M Institute for Healthcare Policy and Innovation.
"There's increasing guidance on approaches to starting treatment in older adults, but less on the next steps to intensify treatment, especially in an older and medically complex population that isn't usually included in clinical trials of blood pressure medication," she said. "How can we increase treatment intensity safely in a population already taking many medications for hypertension and other conditions?"
SEE ALSO: Addressing blood pressure in a new way
"Treatment guidelines do suggest starting treatment with multiple medications, and clinicians are comfortable with an approach of 'starting low and going slow' in older patients," said senior author Lillian Min, M.D., M.S.H.S. "But these results show that in older patients, we have further opportunity to tailor choices in intensifying drug therapy for hypertension, depending on the individual patient's characteristics."
She continued, "Is the patient more likely to stick to a simpler regimen? Then increase an existing medication. Or is the blood pressure very high and the clinician is more concerned about reducing it? Then consider starting a new medication now." Min is a geriatrician at the Division of Geriatrics and Palliative Care at Michigan Medicine, U-M's academic medical center, and the VA Ann Arbor Healthcare System Geriatric Research Education and Clinical Center.
For older adults who already take a range of medications, the added complexity of having to take one more kind of pill may be too much. The risks of polypharmacy, the term for taking multiple medications, are already well-known from other research, Min said. In fact, Medicare covers an annual medication review with a pharmacist for many older adults who take many drugs.
The research was funded by the National Institute on Aging and the Veterans Health Administration. In addition to Aubert and Min, the research team included Jeremy B. Sussman, M.D., M.S.; Timothy P. Hofer, M.D., M.Sc.; William C. Cushman, M.D.; and Jin-Kyung Ha, PhD.
Paper cited: "Adding a New Medication Versus Maximizing Dose to Intensify Hypertension Treatment in Older Adults," Ann Intern Med. DOI: 10.7326/M21-1456

Health Lab
Explore thousands of health news & research stories by visiting the Health Lab homepage for more.
Media Contact

Public Relations
Department of Communication at Michigan Medicine
Stay Informed
Want top health & research news weekly? Sign up for Health Lab’s newsletters today!
Featured News & Stories
Top 7 tips for choosing Medicare prescription drug coverage for 2027

Many older adults make Medicare decisions quickly and most don’t change plans, poll finds
Many hospitals still don’t do enough to prevent UTIs from catheters

Digital alerts support timely treatment decisions of critically ill cardiac patients

Is the United States Lagging Behind Europe in Memory Improvement?